Author Archives: Bob Hansen MD

Unknown's avatar

About Bob Hansen MD

I am a practicing physician, board certified in Anesthesiology and Internal Medicine with Certificate of Special Qualifications in Critical Care. My interests include the effects of lifestyle on health and health care policy.

Chronic Pain: How does it occur and what can be done about it?

I have discussed the effects of nutrition, stress-reduction, sleep, and circadian rhythm on pain in previous posts . I have not yet discussed the theory of how chronic pain develops and persists. This post discusses some of the mechanisms involved in chronic pain as well as therapeutic approaches that have proven to be effective in addressing the root causes of chronic pain and suffering.

THE CENTRAL NERVOUS SYSTEM (BRAIN AND SPINAL CORD) CAN INDEPENDENTLY CAUSE PAIN AND OTHER PHYSICAL SYMPTOMS THROUGH THE DEVELOPMENT OF LEARNED NERVE PATHWAYS. THESE PATHWAYS INCLUDE CIRCUITS WITHIN THE BRAIN AND CIRCUITS CONNECTING THE SPINAL CORD TO VARIOUS PARTS OF THE BRAIN. THEY CAN PRODUCE PAIN EVEN IN THE ABSENCE OF ONGOING TISSUE DAMAGE.

THESE LEARNED NERVE PATHWAYS CAN DEVELOP AS A RESULT OF SEVERAL WEEKS OR MONTHS OF CONTINUOUS PAIN CAUSED BY AN INJURY OR DEGENERATIVE-INFLAMMATORY DISEASE. IF WE EXPERIENCE RELENTLESS PAINFUL IMPULSES COURSING THROUGH THE BODY THESE BOMBARD THE SPINAL CORD AND BRAIN WITH PAINFUL MESSAGES AND OUR BRAIN AND SPINAL CORD EXPERIENCE A CHANGE SIMILAR TO THE CHANGES THAT CAN OCCUR WITH PTSD CAUSED BY ONE OR MORE TRAUMATIC EVENTS.

THESE LEARNED NERVOUS SYSTEM PATHWAYS REPRESENT “NEUROPLASTICITY” MEANING CHANGES IN THE NERVOUS SYSTEM BROUGHT ABOUT BY EVENTS SUCH AS TRAUMA AND STRESS. THEY REPRESENT A “MEMORY” OF THE PAIN, TRAUMA AND STRESS IMPRINTED ON THE NERVOUS SYSTEM. THIS “MEMORY” INCLUDES NEWLY (AND OFTEN PERMANENTLY) FORMED CIRCUITS THAT OFTEN CONNECT VARIOUS PARTS OF THE BRAIN ASSOCIATED WITH PAIN, ANXIETY, DEPRESSION AND ANGER TO PARTS OF THE BRAIN AND SPINAL CORD THAT MEDIATE SENSATIONS OF LIGHT TOUCH AND PRESSURE. THESE CONNECTIONS PRODUCE “ALLODYNIA” WHICH IS A PAINFUL RESPONSE TO A STIMULUS WHICH IS USUALLY NOT PAINFUL. WE CAN ALSO EXPERIENCE “HYPERALGESIA” WHICH IS AN EXAGGERATED PAIN EXPERIENCE, OUT OF PROPORTION TO THE PAINFUL STIMULUS.

THE NERVOUS SYSTEM HAS A BUILT IN “MUFFLER” DESIGNED TO DAMPEN DOWN PAIN MESSAGES BUT IN CHRONIC PAIN THIS MUFFLER BECOMES AN AMPLIFIER THAT NOT ONLY AMPLIFIES THE TRANSMISSION OF PAIN BUT ALSO CONNECTS THIS AMPLIFIED PAIN SYSTEM TO PARTS OF THE BRAIN ASSOCIATED WITH ANXIETY, ANGER, AND DEPRESSION.

ONCE THESE CIRCUITS OR PATHWAYS ARE IN PLACE (“LEARNED”) THEY CAN NOT BE ELIMINATED (“UNLEARNED”). EFFECTIVE PAIN REDUCTION REQUIRES ACTIVATING ON A REGULAR BASIS ALTERNATIVE PATHWAYS THAT ALREADY EXIST SUCH AS THOSE ASSOCIATED WITH PLAY, MUSIC, DANCE, HUMOR, LAUGHING. ACTIVATING OTHER PATHWAYS CAN ALLOW THE PAIN PATHWAYS TO BE “TURNED OFF” OR MUFFLED. AS CHILDREN WE LEARN TO PLAY AND THOSE LEARNED PATHWAYS STAY WITH US FOR LIFE. WITH PRACTICE WE CAN REGULARLY ACTIVATE THOSE BRAIN PATHWAYS AND MAKE THEM AND OTHER PATHWAYS THE PREDOMINANT PATHWAYS OF OUR BRAIN ACTIVITY.

BUT BEFORE WE CAN UTILIZE THE PLEASANT ALREADY-LEARNED PATHWAYS IN THE BRAIN TO CIRCUMVENT THE PAINFUL-ANXIOUS PATHWAYS WE MUST FIRST DEAL WITH OUR ANGER. DEALING WITH OUR NATURAL AND JUSTIFIABLE ANGER REQUIRES FORGIVENESS. UNTIL THE ANGER IS RELEASED AND FORGIVENESS ACHIEVED WE CANNOT MAKE USE OF THE THERAPIES AND STRATEGIES AVAILABLE TO DECREASE AND MANAGE OUR PAIN. ANGER BLOCKS THE PATH TO HEALING AND PAIN REDUCTION.

The brain processes an emotional insult in exactly the same way that the brain processes a physical insult. Stressful life events and our emotional reactions to them may cause pain that is severe. This is why chronic pain becomes worse when we experience a stressful event. Vicious cycles develop as multiple circuits connecting pain pathways to areas of the brain associated with anxiety and depression become activated and stay activated.

COGNITIVE BEHAVIORAL THERAPY: Over the course of months and years, our reaction to chronic pain often includes repetitive negative thoughts. Cognitive behavioral therapy helps us learn techniques to avoid repetitive negative thoughts.

Mindfulness Based Stress Reduction is another technique that can help mitigate the suffering associated with pain. Mindful Meditation practiced 30 minutes per day produces measurable changes in brain activity that can be seen on Functional MRI scans of the brain within 90 days. These changes demonstrate decreased brain activity in areas associated with pain, depression, anxiety and anger. Scientific studies have also demonstrated that MBSR produces improved immune function, reduces blood pressure, reduces heart rate AND improves heart rate variability (an indicator of cardiovascular and metabolic health), improves sleep and provides other beneficial physiologic changes associated with healing and wellness. Yoga and meditation are essential components of an MBSR program.

SLEEP: Pain cannot be managed or successfully treated unless an individual gets 7-8 hours of restorative sleep per night. Sleep hygiene recommendations are an essential part of the path to wellness. Daily exposure to sunlight outdoors early in the day and restoring normal circadian rhythm are essential for pain management. Going to bed at the same time every evening and sticking to a regular schedule is an important part of improving sleep. Early daytime exposure to sunlight and dimming the lights in the evening are also required. Regular exercise (daily walking) is essential. Wearing blue-light blocking glasses for 2-3 hours before bedtime can facilitate sleep. When blue light wavelengths (light bulbs, computer screens, TV screens) hit the retina of the eye a message is immediately relayed to the “internal clock” of the brain that tells the brain there is still daylight. This inhibits the production of melatonin (the “sleep hormone”). Avoiding bright light (especially from TV or computer screens) for 2-3 hours before bedtime is important. If you must watch TV or work on the computer in the evening than blue light blocking glasses or goggles are a must. There are free software programs that will eliminate the blue light from your computer screen and cell phone as an alternative to blue light blockers.

NUTRITION: Pain involves inflammatory pathways. An anti-inflammatory diet is essential for treating pain and providing the nutritional components necessary for healing tissue and establishing better brain chemistry. A  Paleo (also called Ancestral) Diet removes potential sources of inflammation from the diet. If a patient suffers from an auto-immune disorder the more restrictive Autoimmune Protocol version of the Paleo-diet can help put the disease into remission and decrease the inflammation associated with the auto-immune process.

OBESITY AND OVERWEIGHT: Extra fat around the belly and internal organs causes chronic inflammation throughout the body. The fat cells around internal organs and the immune cells that reside alongside the fat cells both produce a steady stream of chemicals that circulate throughout the body stimulating inflammation everywhere. These circulating chemicals are called cytokines and chemokines. Certain cytokines and chemokines cause fatigue, brain fog, and sensitize the nerves, increasing pain. They also interfere with sleep. Weight loss is an essential component to pain reduction for overweight and obese patients. The best nutritional approach to weight loss includes a Paleo Diet with carbohydrate restriction (low carbohydrate, high-healthy-fat whole food diet). Adding medically supervised intermittent fasting (such as an 18- 24 hour fast every 1-2 weeks, consuming only water for 18-24 hours) can also be effective especially combined with a carbohydrate restricted Paleo Diet and lifestyle.

Exercise and Physical Conditioning: Chronic pain causes sedentary behavior which results in physical de-conditioning. This process involves loss of muscle, decreased bone density, shortening of ligaments and tendons and shrinkage of the tissues that envelope muscle. This leads to more pain when physical activity is increased and a vicious cycle is created. This cycle must be broken with a graduated daily exercise and physical conditioning program. If you follow a medically prescribed exercise program you will not damage your body even though it may be painful during the first several days. Exercise also helps to convert the “amplifier” back to a “muffler” in the nervous system.

Below are some links to articles related to this discussion.

Eat clean, live clean.

Bob Hansen MD

Applying modern pain neuroscience in clinical practice: criteria for the classification of central sensitization pain.

Central sensitization and altered central pain processing in chronic low back pain: fact or myth?

How to explain central sensitization to patients with ‘unexplained’ chronic musculoskeletal pain: practice guidelines.

Addressing sleep problems and cognitive dysfunctions in comprehensive rehabilitation for chronic musculoskeletal pain.

Exercise therapy for chronic musculoskeletal pain: Innovation by altering pain memories.

Efficacy of a modern neuroscience approach versus usual care evidence-based physiotherapy on pain, disability and brain characteristics in chronic spinal pain patients: protocol of a randomized clinical trial.

The effect of relaxation therapy on autonomic functioning, symptoms and daily functioning, in patients with chronic fatigue syndrome or fibromyalgia: a systematic review.

Pro-nociceptive and anti-nociceptive effects of a conditioned pain modulation protocol in participants with chronic low back pain and healthy control subjects.

Vagal modulation and symptomatology following a 6-month aerobic exercise program for women with fibromyalgia.

Brain-derived neurotrophic factor as a driving force behind neuroplasticity in neuropathic and central sensitization pain: a new therapeutic target?

The role of central sensitization in shoulder pain: A systematic literature review.

Chronic whiplash-associated disorders: to exercise or not?

Exercise, not to exercise, or how to exercise in patients with chronic pain? Applying science to practice.

Evidence for central sensitization in patients with osteoarthritis pain: a systematic literature review.

Malfunctioning of the autonomic nervous system in patients with chronic fatigue syndrome: a systematic literature review.

Endogenous pain modulation in response to exercise in patients with rheumatoid arthritis, patients with chronic fatigue syndrome and comorbid fibromyalgia, and healthy controls: a double-blind randomized controlled trial.

You may need a nerve to treat pain: the neurobiological rationale for vagal nerve activation in pain management.

Avoidance behavior towards physical activity in chronic fatigue syndrome and fibromyalgia: the fear for post-exertional malaise.

The role of mitochondrial dysfunctions due to oxidative and nitrosative stress in the chronic pain or chronic fatigue syndromes and fibromyalgia patients: peripheral and central mechanisms as therapeutic targets?

Thinking beyond muscles and joints: therapists’ and patients’ attitudes and beliefs regarding chronic musculoskeletal pain are key to applying effective treatment.

Evidence for central sensitization in chronic whiplash: a systematic literature review.

Pain in patients with chronic fatigue syndrome: time for specific pain treatment?

Kinesiophobia, catastrophizing and anticipated symptoms before stair climbing in chronic fatigue syndrome: an experimental study.

Central sensitization in patients with rheumatoid arthritis: a systematic literature review.

Cure diabetes by fasting or eating less sugar and starch? No drugs involved.

Jason Fung is a brilliant Canadian physician who has treated obesity and diabetes with a fasting protocol. Intermittent fasting produces physiologic changes similar to a low carbohydrate ketogenic diet (LCKD). Both approaches have been successfully used to treat diabetes, insulin resistance, obesity and metabolic syndrome. Learn why most medications that are used to treat diabetes do not address the underlying root cause by watching this video.

After watching that video consider the following discussion by Dr. Tim Noakes who cured his own “pre-diabetes” with a LCKD. Dr. Noakes was criticized by his less open-minded colleagues for employing a beneficial lifestyle change that allows most diabetics to reduce or eliminate their medications. Dr. Noakes had followed the “prudent diet” recommended by the USDA and AHA for decades. Despite following that “prudent diet” and exercising regularly by running long distances he had developed “pre-diabetes” (insulin resistance which often leads to type II diabetes). Then he stumbled upon an iconoclastic approach,

So he read more about it and decided to try it. The results were stunning to this physician who became an ardent proponent of carbohydrate restriction.

Now if you have not heard enough, listen to Eric C. Westman, MD, MHS who treats patients and teaches medical students and residents at the Duke University Lifestyle Medicine Clinic.

A paleo diet in combination with carbohydrate restriction is arguably the most beneficial nutritional approach to diabetes, pre-diabetes and obesity. The data that supports this statement grows on a daily basis.

You can read about why a LCKD should be the default diet for diabetes here.

Dietary carbohydrate restriction as the first approach in diabetes management: Critical review and evidence base – Nutrition

Eat clean, live clean.


BOB

Endocrine Disrupting chemicals in food, containers and environment results “in a range of human diseases and abnormalities.”

The findings of four articles recently published in the Journal of Clinical Endocrinology and Metabolism were presented on March 5 at a press briefing held at the Endocrine Society’s annual meeting, ENDO 2015, Despite the incredible public health implications of these four studies little has been reported in the popular press.

I have previously discussed the Environmental Working Group’s list of the Clean Fifteen and the Dirty Dozen toxic chemicals | Practical Evolutionary Health as well as the impact of environmental toxins on our epidemic of auto-immune disease Babies born with more than 200 toxic chemicals in their blood | Practical Evolutionary Health .

The press briefing and the findings of these four studies were reported on-line Endocrine Disruptors Cause Range of Diseases; Cost 157 Billion Euros

The estimated health effects of pesticides, chemicals used in personal care products, aluminum can liners, flame retardants in clothing, mattresses, furniture,  etc., included the following

From pesticides:

  • 59,300 infants born with intellectual disability
  • 28,200 people aged 50-64 years with type 2 diabetes
  • 13 million lost IQ points in each EU country

From Phtalates used in food wraps, cosmetics, shampoos, vinyl flooring

  • 24,800 deaths among 55-64 year old men
  • 618,000 additional assisted-reproductive technology procedures to treat infertility
  • excess of obesity and diabetes among women aged 50 to 64

Flame retardants in electronics, furniture, mattresses:

  • 3290 intellectually disabled children
  • 873,000 lost IQ points
  • 6830 cases of testicular cancer
  • 4615 children born with undescended testes

Other estimates from endocrine disruptors included:

  • 316 autistic 8 year olds EACH YEAR
  • 31,200 ten year olds with ADHD

Here are some snippets from the on-line Medscape report.The economic costs are reported in Euros since this was a study of European data. Bear in mind that the European Union has more stringent environmental protection than the United States. As a result, a study using US data would likely show even greater damage.

The papers cover overall costs of selected disorders attributed to specific endocrine-disrupting chemicals, as well as more detailed analyses of costs related to endocrine-disrupter–linked obesity and diabetes, neurobehavioral deficits/disease, and male reproductive disorders/diseases.

“Limiting our exposure to the most widely used and potentially hazardous endocrine-disrupting chemicals is likely to produce substantial economic benefit,” lead author of the overview study, Leonardo Trasande, MD, from New York University, said at the briefing.

The European Union defines an endocrine-disrupting chemical as an “exogenous substance that causes adverse health effects in an intact organism or its progeny, secondary to changes in endocrine function.”

With exposures occurring via pharmaceuticals, industrial solvents, personal-care products, aluminum-can linings, plasticizers, pesticides, and environmental pollutants, chemicals known to be endocrine disrupting include diethylstilbestrol, polychlorinated biphenyls (PCBs) , dioxins, perfluoroalkyl compounds, solvents, phthalates, bisphenol A (BPA), dichlorodiphenyldichloroethylene organophosphate/organochlorine pesticides, and polybrominated diphenyl.

Affected hormones include estrogen, androgen, thyroid, retinol, aryl hydrocarbon, and the peroxisome proliferator-activated receptor (PPAR) pathway. In all, 13 chronic conditions have strong scientific evidence for causation by endocrine-disrupting chemicals, Dr Trasande said.

“There are safe and simple steps that families can take to limit their exposure to endocrine-disruptive chemicals. They can avoid microwaving plastic. They can avoid eating from aluminum cans or drinking fluids from aluminum cans. They can eat organic. Or even simply air out their homes every couple of days to remove some of the chemical dust…that can disrupt hormones in their bodies.”

Using estimates based on the literature and established statistical methods adapted from those used by the Intergovernmental Panel on Climate Change, Dr Trasande led a 12-member scientific steering committee, which determined that there was probable causation of endocrine-disrupting chemicals for IQ loss and associated intellectual disability, autism, attention-deficit/hyperactivity disorder (ADHD), childhood obesity, adult obesity, adult diabetes, cryptorchidism, male infertility, and mortality associated with reduced testosterone.

Using mid-point estimates for probability of causation, the panel calculated a median cost of €157 billion, or 1.23% of the EU gross domestic product, with a lower median range of €119 billion and a high end estimate of €270 billion.

Dr Trasande summarized results from the four papers at the briefing, including these data points:

  • By health effect, the greatest cost was for neurological problems, including ADHD, at €132 billion. By endocrine-disrupting chemical type, pesticides were the most costly, accounting for €120 billion.
  • Pesticides accounted for 13 million lost IQ points in each EU country, costing €124 billion in earning potential. They were also responsible for 59,300 infants born with intellectual disability (€24.6 million), and 28,200 people aged 50-64 years with type 2 diabetes, at a cost of €835 million.
  • Phthalates, used in food wraps, cosmetics, shampoos, and vinyl flooring, resulted in 24,800 additional deaths among 55- to 64-year-old men, costing €7.96 billion in lost economic productivity; and 618,000 additional assisted-reproductive-technology procedures, costing €4.71 billion, Dr Trasande reported. Phthalates also accounted for an excess of obesity and diabetes among women aged 50 to 64, totaling more than €15.6 billion.
  • Flame retardants used in electronics, furniture, and mattresses resulted in 873,000 lost IQ points, leading to €8.4 billion in lost earning potential; 3290 intellectually disabled children, costing an additional €1.9 billion; 6,830 new cases of testicular cancer, at €850 million; and 4615 children born with undescended testes, at €130 million.
  • Other estimates of burden and disease and costs include 316 autistic 8-year-olds each year from multiple endocrine disrupting chemicals, costing €199 million; 31,200 10-year-olds with ADHD (also from multiple endocrine-disrupting chemicals), at €1.7 billion; and BPA used in aluminum-can linings and thermal-paper receipts, being associated with 42,400 obese 4-year-olds at an annual cost of €1.54 billion.

Dr Trasande said that a similar analysis for the United States would be “the logical next step” and that he would anticipate analogous findings, although there are some differences. Brominated flame retardants are more stringently limited in Europe, for example, but levels of phthalates have decreased 17% to 37% in the United States between 2001 and 2010.

Keep in mind that these studies were published in the peer-reviewed Journal of Clinical Endocrinology and Metabolism. They do not represent a governmental agency report, which is frequently tainted by the influence of lobbyists and scientists with conflicts of interest. Whether the European governments respond to this data in a meaningful way remains to be seen. Given the Republican majority in both the US Congress and US Senate as well as the sad state of journalism in the US it is likely that this scientific data will fall on deaf ears.

Nevertheless, we all have the opportunity to educate ourselves about these dangers to the health of our families and make changes in our daily lives that might limit the damage to our personal health and the health of those we love.

Do not drink water from plastic bottles. Do not drink soda or fruit juices from plastic or aluminum containers. Do not microwave food in plastic containers or store warm food in plastic containers. Eat organic vegetables and fruits whenever possible and avoid especially non-organic produce from the Dirty Dozen

Despite the manufacturers claims to the contrary, BPA used to line aluminum cans is not safe, same for BPA used in thermal paper receipts. “BPA free” hard plastic containers and metal containers lined with BPA replacements will likely prove to be unsafe in the future.

That “new-car” smell and “new-furniture” smell may contain endocrine disrupting flame retardants off-gassing. So open your windows and get rid of those odors, use HEPA air-filters at home. Consider having your old furniture reupholstered instead of buying new furniture. Apply only safe personal care products to your body (visit the EWG website for more information)Consumer Products | Environmental Working Group

Live clean, eat clean.

BOB

Lamb Saag Gosht, Spicey Carrot Tagine, Cauliflower Rice

I just ate a most delicious paleo meal, crafted by my lovely wife Kathie.

DSC_0041

The lamb and spinach dish on the left has some Indian spices. It comes from nom nom paleo.

Saag Gosht (Lamb with Spinach Sauce) | Award-Winning Paleo Recipes | Nom Nom Paleo®

On the right there are two recipes. Kathie used a cauliflower “rice” recipe from the Ancestral Table cookbook. (no rice, just cauliflower, it has the consistency of cous cous)

Ancestral Table

Here is the recipe.

Recipe Cauliflower Rice

She altered a tagine carrot recipe to eliminate the chick peas and made it paleo and served the tagine carrots over the cauliflower rice.

Recipe Spicey Carrot

Tagine Recipe Book

Wow was it good.

We had a laugh about the comments left on nom nom paleo about how delicious the “marrow” is. This is a lamb neck recipe. The “marrow” is actually spinal cord, nutrient dense.

Eat clean, live clean, spend time outdoors with those you love, meditate, exercise wisely and rest. Get plenty of restorative sleep.

BOB

Why do our tax dollars continue to subsidize death, disability and disease?

Yesterday I posted a comment on Medscape after reading an article Longtime Dietary Fat Advice Unsupported by Data: Analysis . Medscape is a website with articles and news written for physicians and other health professionals. Anyone can access this information by creating a user name and password, there is no fee.

Here is my comment. It is long and technical. I will provide an explanation in lay terms after quoting myself.

Sugar, especially HFCS (high fructose corn syrup), used in so many foods is more inflammatory than saturated fat. Grass fed meat from ruminants has a fatty acid mix that is exactly the same as wild game, which we evolved to eat, along with tubers, green leafy vegetables, and fruit in season. Excess refined fructose intake AND use of modern refined “vegetable oils” along with non-healthy grains combine to cause excess caloric intake, NAFLD (non-alcoholic fatty liver disease), obesity, metabolic syndrome and CAD (coronary artery disease). N6 PUFA (omega six polyunsaturated fatty acids) are easily oxidized. N3 PUFA (omega 3 fatty acids) despite greater number of double bonds are protected from oxidation in cell and Lipoprotein membranes by plasmalogens as opposed to linoleic acid which is not easily  incorporated into plasmalogens. The PUFA in vegetable oils (linoleic acid) is the FA (fatty acid) that is oxidized on LDL particles and remnant particles, stimulating monocytes to transform to macrophages and then foam cells. The USDA, ADA and AHA have had it upside down for decades and they still fail to admit folly. We evolved for > 1 million years without grains and they have contributed to disease. Per calorie fresh vegetables have five times the amount of fiber compared to whole grains. We do not need grains and would be better without them. They contain anti-nutrients and wheat, hybridized in the 1980s to a storm resistant dwarf plant, now has 50 times more gluten/gliadin than the old wheat. This has generated more gluten intolerance and celiac. Our greatest nutritional threats to public health include refined sugar, carbohydrates predominantly from grains and refined vegetable oils. Vegetable oils are not healthy, we did not evolve to eat them. N3 FAs are anti-inflammatory but have been competing in our diets with a sea of inflammatory N6 PUFA from unnatural refined and easily oxidized “vegetable oils”. Even though PUFA can reduce LDL-C they wreak havoc by creating ox-LDL particles which initiate the cascade of atherosclerosis. Substituting SFA (saturated fatty acids) with PUFA results in increased levels of Lp(a) and oxLDL in humans, not a good thing. Close the feed lots, stop government subsidy of corn, wheat, dairy and soy, eat meat from grass fed ruminants, wild seafood, fresh organic vegetables and fruits in season. Nibble on tree nuts. Stop creating carcinogens with high dry heat cooking methods and we will watch obesity, insulin resistance, metabolic syndrome and atherosclerosis melt away.

That was my comment. Here is some explanation.

I have previously discussed the pro-inflammatory nature of refined “vegetable oils”. “Vegetable oils” are actually not from vegetables, they are from grains, seeds and legumes. The two major sources of excess omega six polyunsaturated fats in the American diet are corn oil and soy oil marketed by various brand names such as Wesson. They are major components of margarine and other butter substitutes and are present in most salad dressings. Most salad dressings sold in our supermarkets contain high levels of easily oxidized unhealthy refined “vegetable oils” and HFCS. The use of these salad dressings converts a healthy salad into a vector for disease.

The major source of caloric sweeteners in our food and beverages is high fructose corn syrup. Both corn (oil and sugar) and soy predominate our processed food supply because they are cheap. They are cheap because our tax dollars subsidize their production. This subsidy started during the Nixon administration. Once a food subsidy is put in place it is very difficult to eliminate, Big Agriculture provides a deep pocket for lobby money and our elected officials from the mid-west bread-basket respond to $$.

Another major source of disease causing elements in the standard American diet is highly refined flour from wheat. Doctors Davis and Perlmutter discuss the problems associated with wheat-flour foods in their books Wheat Belly and Grain Brain respectively. The production of wheat has also been subsidized since the Nixon administration.

Wheat is not what it used to be. A new dwarf hybrid wheat has predominated the US market since the 1980s. Bread and pasta are not what they used to be when great grand-mother made her own bread and pasta in the kitchen from coarsely ground whole flour. But even if we all went back to making our own whole-grain bread and pasta from locally ground pre-1980s wheat, bread, pasta and pastry would still present a health risk because of issues related to intestinal permeability, auto-immune disease (now epidemic in the USA), and the presence of nasty lectins and phytates (discussed in my manifesto and previous posts).

The Medscape comment quoted above describes  adverse consequences caused by replacing saturated fat in the diet with “vegetable oils”. This is a complex subject and I will try to be brief for now but promise to expand on this in a future post.

Many factors contribute to atherosclerosis, heart attack and stroke. Sedentary lifestyle, stress, inadequate restorative sleep, smoking and poor dietary choices top the list. These factors also contribute to obesity, diabetes, metabolic syndrome, insulin resistance and many cancers.

DIETARY FACTORS:

The combination of sugared foods and beverages (predominantly sweetened with HFCS), refined flour foods, and excess consumption of the PUFA in “vegetable oils” TOGETHER  contribute to the formation of plaque in the walls of our arteries (atherosclerosis).

How does this happen?

LDL (low density lipoprotein) is a particle that transports cholesterol and triglycerides through our blood to our organs. This particle is comprised of a core and a surrounding membrane.  Here is a picture.
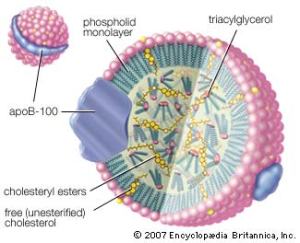
LDL 2

The core contains cholesterol in a storage form (esters) and triglycerides. The outer membrane includes a large protein called apoprotein B-100, “free” cholesterol molecules and phospholipids. The phospholipids contain fatty acids, including PUFA.

LDL has been demonized as “the bad cholesterol” and that demonization has mislead the public.

hdl_ldl good guy bad guy

LDL is the major lipoprotein in our blood but there are others that have different names.

Cholesterol is cholesterol, whether it is carried in LDL or HDL. When carried in the core of a lipoprotein it is carried as a cholesterol ester. 80% of the cholesterol in an LDL particle is carried as an ester in the core. 20% is carried as “free” cholesterol on the outer surface or membrane.

LDLand cholesterol molecule

HDL (high density lipoprotein) is smaller and denser. HDL has been called “the good cholesterol”, another misnomer.

HDL particles, when they are functioning correctly can protect us from atherosclerosis but in patients with diabetes, obesity, and insulin resistance, HDL particles do not function well and in fact probably contribute to disease. (More about that in a future post)

But back to LDL.

Although the risk of cardiovascular disease is correlated with the amount of cholesterol carried by LDL in our blood (referred to as LDL-C), the total amount of cholesterol shuttled by LDL particles is much less relevant than one would be led to believe given the great use of statin drugs to lower LDL-C.

The short version is as follows.

Compared to LDL-C, a much better predictor of cardiovascular disease is the amount of “modified” LDL particles circulating in the blood. Oxidized LDL particles are one form of “modified LDL”. LDL can also  be modified by excess blood sugar levels (especially from HFCS). This modification is referred to as glycosylated or glycated LDL. In this latter form of modification, the major protein on the outer membrane of the LDL particle (apo B 100 in the picture above) becomes attached to a sugar and the result is an LDL particle that is not easily cleared by normal processes. The modified LDL is not “recognized” by the LDL receptors that act as entry points into our cells for proper processing. The result is that the glycated LDL particles circulate longer and are more likely to use up their anti-oxidants (Vitamin E and  Co-enzyme Q 10).

As a result glycated LDL are more likely to become oxidized. That is not good because oxidized LDL sets up a cascade of unhealthy events.

The portion of the LDL particle that becomes oxidized is the fat (fatty acid) from “vegetable oil”, specifically the fatty acid called linoleic acid. This fatty acid has two double bonds making it more likely to be oxidized than for example oleic acid, the major fatty acid in extra virgin olive oil which has only one double bond.

The double bonds between the carbons in the fatty acids are unstable and easily oxidized. The single bonds in saturated fat do not get oxidized.

All other things being equal (and you will see that they are not), the more double bonds in a fatty acid the greater chance for oxidation.

Here is a picture showing the linoleic acid, also called linoleate, on the outer membrane of the LDL particle.
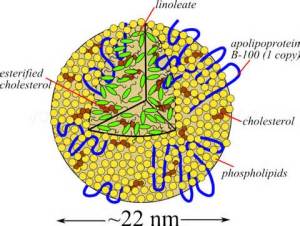
LDL with linoleate

And here is a picture that shows the phospholipids that contain the linoleic acid.
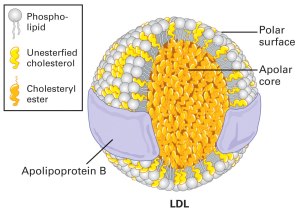
LDL 3

Let’s say it again. The fatty acid found in “vegetable” oil, linoleic acid, is easily oxidized because it has two double bonds.

Saturated fats are not oxidized because they contain no double bonds.

The part of the LDL particle that becomes oxidized is the fatty acid that comes from “vegetable oils”.

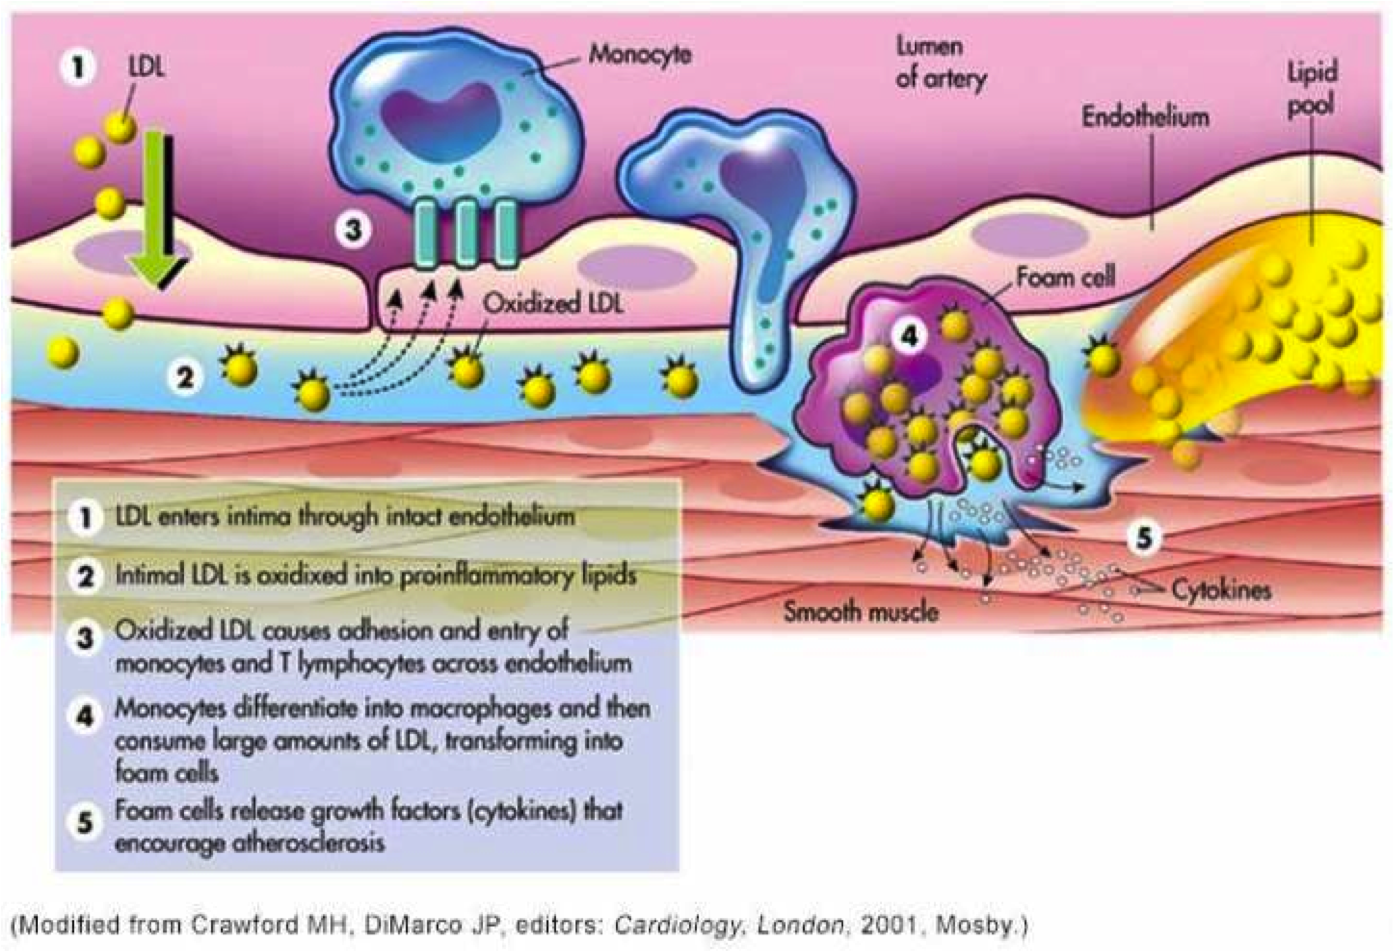
A particular kind of immune cell (white blood cells called monocytes) have  special receptors for oxidized LDL particles. When ox-LDL are “seen” by these monocytes, the monocytes become transformed into macrophages. Macrophages are designed to destroy bacteria that invade our bodies. The oxidized LDL particles resemble the structures of invading bacteria. The macrophages, with very specialized receptors for oxidized LDL, “swallow” the LDL particles and release toxic chemicals to destroy “the invader”.  The macrophages then become “foam cells” in the walls of our arteries, initiating the creation of plaque. Here is a picture.
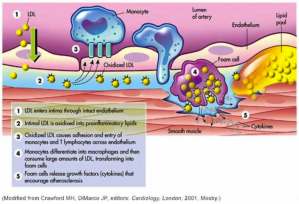
ldl_mechanisms oxidation in vessel wall

This picture depicts the oxidation occurring in the wall of the artery after LDL particles have penetrated the wall. However LDL particles can and do become oxidized while still circulating in the blood and these oxidized particles can stimulate monocytes to transform into macrophages and gobble up the oxidized or modified LDL while these particles are still circulating in the blood.

How and whether unmodified LDL particles cross the wall of arteries into the “sub-endothelial” area remains an unsolved complex issue. The picture above implies that LDL particles simply move across the endothelial cells that line the wall of the artery but that is a presumption.

Clearly, macrophages that have “swallowed” modified LDL particles have mechanisms to work their way between the junctions formed by adjacent endothelial cells.

This is an important distinction because many cardiologists believe that what drives atherosclerosis is a mass effect. The greater the number of LDL particles, the more likely they are to cross the endothelial barrier, get oxidized and retained and start the process of plaque formation. However the process is much more complex and not clearly understood.

We do not yet know or understand completely the factors that influence the permeability of the endothelium to Lipoprotein particles. We do know that modified (oxidized and glycated LDL) disrupt the protective surface of endothelial cells which is called the glyocalyx. Other factors that disrupt the glyocalyx include high blood sugars, dramatic fluctuations in blood pressure (too high or too low), oxidative stress, infections, and circulating endotoxin (which is governed by intestinal permeability).

It is clear from several studies that modified (oxidized) LDL as a single variable predicts cardiovascular disease and heart attacks with much greater accuracy than LDL-C (total cholesterol content of LDL particles). It is also clear that monocyte receptors are specific for modified LDL and that the  process that initiates the cascade of events that leads to plaque formation involves the interaction between modified lipoprotein particles and the immune system (monocytes).

Now here is another twist.

Omega 3 fatty acids in fish oil are considered “heart healthy”. They help prevent heart attacks and strokes. They also decrease inflammation throughout the body thereby producing many health benefits.

BUT OMEGA 3 FAT HAS MORE DOUBLE BONDS THAN OMEGA 6 FAT (LINOLEIC ACID) YET THEY HELP PROTECT THE HEART. HOW CAN THAT BE?

How do they avoid contributing to atherosclerosis? Are they not even more readily oxidized than linoleic acid?

The simple answer is no.

The major reason is that the omega three fatty acids are protected by “plasmalogens” which are important components of our LDL particle outer membranes. Plasmalogens are found in the membranes of lipoprotein particles and in the membranes of human cells. Because of their chemical structures, omega three fats are easily incorporated into plasmalogens which protect the double bonds of omega three fats from oxidation. Linoleic acid, the predominant component of “vegetable oils” is not easily incorporated into the protective arms of plasmalogens.

This selective protection is well described on pages 141-142 of  “The Fats of Life”, written by Dr. Glen Lawrence and published in paperback in 2013. (link below)

I asked Dr. Lawrence about this issue in an email and here was his response.

“The omega-3 fatty acids are preferentially incorporated into plasmalogens, which act as antioxidants due to the double bond adjacent to the ether linkage of these phospholipids. This structure would tend to scavenge free radicals or reactive oxygen species near the surface of the membrane, rather than allowing them to penetrate deeper in the membrane where the double bonds of PUFA are located. This makes any polyunsaturated fatty acids attached to the plasmalogens more resistant to oxidation than they would be in a regular phospholipid. See pp 141-142 of The Fats of Life. The shorter chain and less unsaturated linoleic acid does not tend to be incorporated into plasmalogens.”

In summary:

  1. “Vegetable oil” is actually not oil from vegetables but rather a highly processed and refined oil. This oil contains primarily the easily oxidized omega 6 PUFA (polyunsaturated fatty acid) linoleic acid. Oxidation can occur during manufacture,  before consumption while sitting in the bottle, but especially during high heat cooking (fried foods). Oxidation can also in your body as this fat circulates in your blood on the membrane of lipoprotein particles.
  2.  LDL particles are the major lipoprotein particles that shuttle cholesterol and fatty acids (in in the form of triglycerides) through our bodies in our bloodstream.
  3. Modified LDL particles (glycated and/or oxidized LDL) stimulate monocytes (immune cells) to transform into macrophages and gobble up the modified LDL. In addition, glycated LDL particles are more easily oxidized because they circulate longer in our blood.
  4. Macrophages become filled with modified LDL. These are called foam cells. Foam cells  initiate a cascade of events that lead to the formation of plaque in the walls of our arteries.
  5. The part of the LDL particle membrane that becomes oxidized is the phospholipid that contains linoleic acid which comes from “vegetable oils”
  6. High amounts of sugar, especially HFCS, and highly refined flour foods in our diets cause larger blood sugar fluctuations than whole foods and therefore contribute to the glycation of LDL particles. This glycation leads to more oxidation of LDL. In this manner HFCS and refined flour foods contribute to the process of atherosclerosis.
  7. High amounts of sugar, HFCS and refined flour foods also contribute to obesity, insulin resistance and diabetes which then increase the risk of heart attack and stroke.
  8. Several factors contribute to the disruption of the glycocalyx which is the protective surface of the endothelial cells that line our arteries. These include but are not limited to modified LDL, inflammation, high blood sugars, abnormal fluctuations in blood pressure, circulating endotoxin (associated with increased intestinal permeability), infections. Disruption of the glycocalyx contributes to the formation of plaque (atherosclerosis).
  9. Modified LDL particles might also migrate through the junctions that connect adjacent endothelial cells either inside macrophages or on their own. Many factors, known and unknown likely determine the susceptibility or permeability of these junctions to this migration.

These are the major points, but there is allot more to discuss. Substituting “vegetable oils” for saturated fat in our diets not only increases the amount of oxidized LDL but also increases a dangerous lipoprotein called Lp(a). On third of Americans have an amount of Lp(a) that is considered “high risk” for heart attack and stroke. More about that in a future post.

Then there is the process of an actual heart attack or stroke which involves disruption of plaque and the creation of a blood clot that ultimately disrupts the flow of blood and the death of heart or brain tissue. The susceptibility of plaque to disruption is a huge topic that involves high blood pressure, diabetes, insulin resistance, oxidative stress, inadequate sleep, and stress to name a few. So much more to discuss.

But getting back to the title of this post, why don’t you ask your elected representatives why our tax dollars continue to subsidize nutritional root causes of death, disability and disease?

Here are some links to papers and books that support the discussion above.

Circulating Oxidized LDL Is a Useful Marker for Identifying Patients With Coronary Artery Disease

Cholesterol deposition in macrophages: foam cell formation mediated by cholesterol-enriched oxidized low density lipoprotein.

Erythrocyte fatty acid profiles can predict acute non-fatal myocard… – PubMed – NCBI

Changes in Dietary Fat Intake Alter Plasma Levels of Oxidized Low-Density Lipoprotein and Lipoprotein(a)

Low-density lipoprotein subclass patterns and risk of myocardial in… – PubMed – NCBI

Subendothelial Lipoprotein Retention as the Initiating Process in Atherosclerosis

Oxidative susceptibility of low density lipoprotein subfractions is… – PubMed – NCBI

Effects of linoleate-enriched and oleate-enriched diets in combinat… – PubMed – NCBI

Enhanced oxidative susceptibility and reduced antioxidant content o… – PubMed – NCBI

Susceptibility of small, dense, low-density lipoproteins to oxidati… – PubMed – NCBI

Modulation of Endothelial Glycocalyx Structure under Inflammatory Conditions

Oxidized Lipoproteins Degrade the Endothelial Surface Layer

S1P Control of Endothelial Integrity

Mechanical control of the endothelial barrier. – PubMed – NCBI

Therole of actin-binding proteins in the control of endothelial bar… – PubMed – NCBI

The Fats of Life, Dr. Glen Lawrence

Functions of plasmalogen lipids in health and disease

Grain Brain: The Surprising Truth about Wheat, Carbs, and Sugar–Your Brain’s Silent Killers: David Perlmutter, Kristin Loberg: 9780316234801: Amazon.com: Books

Finally a quote from the Dali Lama (thanks to my cousin Diane for bringing this to my attention).

“Man. Because he sacrifices his health in order to make money. Then he sacrifices money to recuperate his health. And then he is so anxious about the future that he does not enjoy the present, the result being that he does not live in the present or the future, he lives as if he is never going to die, and dies having never really lived.”

Eat clean, live clean, sleep well, exercise wisely, rest often, enjoy the company of loved ones, spend time outdoors and live in the present.

BOB

The Dirty Dozen and The Clean Fifteen, from the Environmental Working Group

I’ve been working on two projects that have kept me from blogging. The first project was a lecture given at the January meeting of Physicians for Ancestral Health. The second project, still on-going, developed out of a new working relationship with Dr. Tommy Wood who I met at the PAH meeting. I will be sharing more about both of these in future posts.

But today I am returning where I left off with my last post about toxins in our babies and our environment. i promised to discuss the The Dirty Dozen and The Clean Fifteen, both trademarks of the Environmental Working Group . So here it is.

The EWG developed these lists to help individuals make informed purchasing decisions  relative to organic vs non-organic vegetables and fruits. The EWG analyzed data from testing for residuals of pesticides. So if you cannot afford to purchase all organic produce, you can get the most benefit from your dollar by limiting your non-organic produce to the “clean” list and purchasing only organic from the “dirty list”.

Highlights of Dirty Dozen™ 2014

Each of these foods contained a number of different pesticide residues and showed high concentrations of pesticides relative to other produce items.

EWG’s Dirty Dozen™ list of produce includes

  1. apples,
  2. strawberries,
  3. grapes,
  4. celery,
  5. peaches,
  6. spinach,
  7. sweet bell peppers,
  8. imported nectarines,
  9. cucumbers,
  10. cherry tomatoes,
  11. imported snap peas
  12. potatoes.

“In particular:

  • Every sample of imported nectarines and 99 percent of apple samples tested positive for at least one pesticide residue.
  • The average potato had more pesticides by weight than any other food.
  • A single grape sample contained 15 pesticides. Single samples of celery, cherry tomatoes, imported snap peas and strawberries showed 13 different pesticides apiece.”

 Dirty Dozen PLUS™

For the third year, EWG expanded the Dirty Dozen™ with a Plus category to highlight two foods that contain trace levels of highly hazardous pesticides. These foods do not meet traditional Dirty Dozen™ ranking criteria but were frequently contaminated with insecticides that are toxic to the human nervous system. EWG recommends that people who eat a lot of these foods buy organic instead.

  1. Leafy greens – kale and collard greens
  2. hot peppers

The Clean Fifteen™ Relatively few pesticides were detected on these foods, and tests found low total concentrations of pesticides.

EWG’s Clean Fifteen™ for 2014 – the produce least likely to hold pesticide residues – are

  1. avocados,
  2. sweet corn,
  3. pineapples,
  4. cabbage,
  5. frozen sweet peas,
  6. onions,
  7. asparagus,
  8. mangoes,
  9. papayas,
  10. kiwis,
  11. eggplant,
  12. grapefruit,
  13. cantaloupe,
  14. cauliflower
  15. sweet potatoes.

 “Notable findings:

  • Avocados were the cleanest: only 1 percent of avocado samples showed any detectable pesticides.
  • Some 89 percent of pineapples, 82 percent of kiwi, 80 percent of papayas, 88 percent of mango and 61 percent of cantaloupe had no residues.
  • No single fruit sample from the Clean Fifteen™ tested positive for more than 4 types of pesticides.
  • Detecting multiple pesticide residues is extremely rare on Clean Fifteen™ vegetables. Only 5.5 percent of Clean Fifteen samples had two or more pesticides.”

At the PAH meeting I spoke with Dr.Tommy Wood and Darryl Edwards , both from England, about food choices in Europe vs the USA.  We had this conversation while eating out and asking the waitress questions about the sources of food. They both commented that when eating in England or the European Union they are not often concerned about food quality because the use of pesticides, hormones, and antibiotics is so reasonably regulated. Most produce is considered organic or close to organic. In addition most meats are grass-fed, free of or low in exogenous hormones and antibiotics, free of excess pro-inflammatory omega six fat and contain more anti-inflammatory and beneficial omega 3 fat, similar to the fat profiles of wild game. Concentrated Animal Feeding Operations (CAFOs) so prevalent in the US are rare in the European Union.

Food for thought and thoughts about food.

Eat clean, live clean and prosper.

Bob

Babies born with more than 200 toxic chemicals in their blood

The  Environmental Working Group (EWG) is a non profit organization devoted to protecting the public from one of our greatest health threats, pollution in all of it’s forms. The EWG supported a study in which newborn infants were tested for known industrial and agricultural toxic chemicals. All of the infants had > 200 and some up to 300 toxic chemicals found circulating in their blood at birth. These babies were not born to parents living in or near toxic waste dumps, or working in dangerous industrial environments. They were born to parents living like you and me. You can read about this and many other issues here.

The 1976 Toxic Substances Control Act grandfathered >70,000 industrial and agricultural chemicals already in use as “safe” and provided for no effective standardized testing requirements for the introduction of new chemicals. Heather White, Executive Director of the EWG was recently interviewed for an  Autoimmune Summit. I have attended this health related summit on-line while recovering from my surgery and was shocked to hear and then read about out environmental exposure and lack of protection.

We often think about pollution and environmental toxins as contributing to cancer, birth defects, asthma and similar problems but auto-immunity is another problem with links to our toxic exposure.

During the Auto-Immune Summit Aristo Vojdani, Ph.D., M.Sc., M.T. scientist and editor of a peer-reviewed journal on auto-immunity, estimated that 60% of auto-immune diseases are “triggered” by environmental toxins, 30% triggered by dietary components, and 10% triggered by infectious disease. He distinguished triggers from predisposing factors which represent the physiologic milieu that leads to auto-immunity. This terminology of triggers vs. predisposing factors may seem confusing and arbitrary. In a nutshell, underlying the molecular mimicry theory of auto-immunity is “leaky gut”.  The “gateway to autoimmunity” is “leaky gut” (increased intestinal permeability) which allows foreign substances to cross the intestinal barrier, enter the circulation and challenge our immune system. Leaky gut  has many contributing factors including but not limited to diet, stress, gut dysbiosis and infections.  Although the % of auto-immune disease that is “triggered by” environmental toxins (versus diet and infections) remains speculative, there is mounting evidence that all of these factors contribute to greater or lesser degrees in various patients.

The paleo community has often stressed the importance of eliminating specific foods and replacing sugar laden flour foods with nutrient dense foods. But emphasis has also been placed on eating organic foods to avoid pesticides, herbicides and hormones.

Dr Vojdani has suggested that in addition to the gut-immune related mechanisms of molecular mimicry, environmental toxins, especially heavy metals, BPA and organic solvents,  act not only has foreign invaders stimulating the immune system but also stimulate the immune system by causing tissue damage directly and thereby presenting damaged or transformed tissue to the immune system as foreign. Environmental toxins do not require a leaky gut to enter our bodies. Many are absorbed through our lungs and skin, and many are directly absorbed through our guts even in the absence of a “Leaky gut”. Heavy metals including mercury, lead and cadmium do not require a leaky gut for intestinal absorption, nor do pesticides, herbicides or hormones administered to the animal we consume. They wreak havoc not only by directly damaging our organs but also by altering our immune system.

Dr Noel Rose, Director of Center for Autoimmune Research (John’s Hopkin’s University) and Dr. Ahmet Hoke, Director, Division of Neuomuscular Disease (John’s Hopkins NIMH Center) opine that our rising rates of auto-immune disease are the result of our “unsuccessful adaptation to new environmental agents”. (See Forward written in Last Best Cure | Donna Jackson Nakazawa.)

The  Government Accountability Office (GAO) is the Federal Government’s internal watchdog agency. A GAO report ( U.S. GAO – Environmental Justice: EPA Needs to Take Additional Actions to Help Ensure Effective Implementation) revealed that 85% of the new chemicals introduced into our environment are not accessed for safety. The  Environmental Protection Agency receives 90 days notice prior to the introduction of new chemicals (industrial, agricultural, etc). Industry does not have the burden of proof relative to safety. Instead, the EPA must determine, within 90 days, if a new chemical is “safe”. Shouldn’t it be the other way around?

Beyond that issue we have the problem of multiple  low grade simultaneous exposures. If a given level of toxin is “safe” based on short term studies of animals or humans, how do we know that a combination of hundreds or thousands of toxins over many years are “safe”. Likewise, if  air concentrations or water concentrations of a single toxin are deemed “safe” how can we possible test the combined effects of hundreds and thousands of environmental toxins in our air, water, soil and food?

The EPA, created under the Nixon administration, was decimated during the Bush administration when budget cuts resulted in the loss of > 50% of it’s senior scientists. With that executive action most of the EPA’s institutional memory was lost and along with it many of the already limited safeguards we had in place.

The concept of “eating clean” minimizes exposure to the potentially harmful effects of anti-nutrients  and immune stimulants (harmful plant lectins and saponins, excess phytic acid, excess omega 6 fatty acids) and more importantly encourages the consumption of nutrient dense foods (lots of colorful vegetables, grass fed meats, wild seafood). But “eating clean” also requires avoiding environmental toxins, including pesticides and herbicides.

To achieve that goal within a budget you can consult the EWG’s lists of foods that have the most and the least amount/variety of pesticides/herbicides. These lists are called the “dirty dozen” and the “clean fifteen”.

To avoid heavy metal exposure (especially mercury) eat seafood that is low on the food chain (less opportunity to accumulate mercury in their tissue). Many people do not realize that most of the mercury in our seafood comes from burning coal. Multiple heavy metals are present in coal. When coal is burned to generate electricity the heavy metals are released into the air and are then washed into our rivers, streams, lakes and oceans where they can accumulate in fish. As the heavy metals work up the food chain they accumulate in tissues. The best/safeest sources of healthy omega three fats are in smaller cold water fish (sardines, anchovies, small mackeral, salmon, trout). And do not forget oysters, scallops,  mussels,  and clams which may have less amounts of omega 3 fats but are safe with respect to heavy metals being low down on the food chain.

The concept of “living clean” involves more than being selective about food and cooking techniques. It involves avoiding exposure to toxic chemicals which can be found in our water (drinking and bathing), air, soil, clothing, furniture, make-up, deodorant, toothpaste and household cleaners. You can learn about these exposures at the EWG’s website. Consumer Guides | Environmental Working Group

Here is a fact that might get your attention, 90% of red lipstick has mercury in it. That’s right, 90%. Every day women around the world are painting their lips with lipstick that has mercury. The average American uses 10-12 personal care products per day which exposes us to 120 or more toxic ingredients. The law that regulates personal care products was written in 1938 (after a woman became blind from using mascara). It needs to be updated and there is much lobbying against better regulation (lots of money in personal care products an make-up). In the meantime we need to be more aware about what we put on and in our bodies.

Our environment is filled with “endocrine disruptors” which mimic and interfere with our hormones. The most common one is BPA (plastic) which has estrogen like effects.

What are our greatest exposures to BPA? Answer: plastic lids on coffee/tea to-go cups, plastic bottles of soda and plastic bottles containing citrus juices. Heat and acid both leech BPA (and probably other toxins) out of plastic into the liquids we drink. The most acidic beverage by far is SODA (as low as pH 2.2). So toxic chemical exposure is yet another reason to avoid soda. Do not serve your guests soda or water in plastic containers at parties. Set an example. Store your foods in glass containers and especially do not put warm or hot food into plastic containers. Get a water filter for your drinking water. Some even go so far as to get a water filter for their showers and baths.

Finally, flame retardants (furniture and clothing) required by law represent major health hazards by filling the air of our homes and exposing our skin to toxic substances. Mothers and toddlers have an estimated 3 times greater risk for this exposure which has been linked to neuro-development disorders, ADHD and endocrine disruption. Firefighters have very elevated levels of toxic chemicals derived from flame retardants. Some patients with a variety of illnesses have seen improvement in symptoms by having their furniture re-upholstered with coverings that do not contain flame retardants (anecdotal reports). Consider getting a HEPA air filter for your home and office. Remember hurricane Katrina? Remember the great number of illnesses reported by families made homeless by Katrina who were relocated to live in temporary portable housing. Those buildings were releasing formaldehyde and other toxic chemicals and produced illness within just a few days.

In my next post I will provide the “dirty dozen” and “clean fifteen” lists to help you make decisions about organic food purchases if you cannot afford to purchase 100% organic. In the meantime check out the EWG website. Also coming soon is a recipe for tumeric-ginger tea/marinade as an anti-inflammatory alternative to NSAIDs.

Live Clean and Prosper

Bob Hansen MD.

A Paleo physician’s journey through major surgery

At age 46 I had a total hip arthroplasty (THA). Metal and plastic components replaced my hip joint (the stem, ball and socket of the hip). I am convinced that if I had adopted a Paleo lifestyle at age twenty instead of age 58 I would have not needed that surgery. But more about that another time.

On Monday I underwent a revision of that surgery to replace some components, scrape out bad bone, remove inflamed joint lining, flush out plastic debris, and place some bone grafts into areas where bone cysts had formed. The surgery was necessary because the plastic debris from my first artificial joint had stimulated my immune system in a way that caused my macrophages (white blood cells) and osteoclasts (a special kind of bone cell) to start destroying the bone around my hip socket. This process is called osteolysis.

Our immune cells evolved to destroy and consume bacteria and viruses, not plastic powder. So as the plastic liner of my hip prosthesis wore down, the plastic debris provided a constant source of inflammation, stimulating my immune system to get rid of a foreign invader. The bone around my prosthesis got caught in friendly fire. This problem does not seem to occur since a newer form of plastic, having only 10% the wear rate of the old plastic has been introduced. Time will tell if that proves to be true.

To prepare for surgery I reviewed my Paleo behavior with respect to diet, sleep, exercise, stress reduction and outdoor time. My exercise routine was already very reasonable. I had been strictly avoiding grains (except for occasional white rice) and legumes but did include some fermented dairy (kefir and cheese) and wine. So I eliminated all dairy and all alcohol. Sleep has always been an issue because as a physician I take call and sometimes work through the night with emergency cases.

My last call night was 3 weeks before surgery and I was up all night. The next day I flew to NJ for two important events (a reunion and a wedding) both of which were definitely not Paleo environments. A flight cancelation required more sleep deprivation in order to reach my first event on time. That sleep deprivation in combination with the changes in time zone disrupted my circadian rhythm so upon returning home two weeks before surgery I knew I had to play catch-up to be ready for surgery. I avoided alcohol except for a few drinks at my brother’s wedding and violated the wheat prohibition once with a piece of wedding cake.

When I returned to California I was 6 pounds heavier and jet lagged. I promptly got an upper respiratory infection (probably acquired on my flight home) which started in my throat and nose and went to my lungs.

So now I am jet-lagged and infected just two weeks from surgery. Not a good situation.

Thereafter I was strictly Paleo in diet, sleep, and stress reduction (yoga and meditation) but had to limit exercise to yoga and walking in order to fight the infection and prepare for surgery. I spent as much time walking outdoors as was feasible and focused on eight hours sleep each night. After one week I was beating the URI so I decided to do two 30 minute sessions of resistance training during the last week before surgery.

By the day of surgery the URI was completely cleared and I was down 6 pounds to my baseline.

I self administered my own pre-operative medication protocol (designed to mitigate post operative pain) and received a spinal anesthetic from my friend and colleague using a combination of local anesthetic and a small dose of spinal morphine. The latter can provide pain reduction for up to 24 hours after surgery.

So here is the amazing result.

5 hours after surgery I walked without pain using a walker bearing full weight on the surgical leg. I walked again that evening without pain. I knew this was the honeymoon period because the spinal morphine was still protecting me.

The next morning the honeymoon was over but I was still able to walk with full weight bearing without any pain medications and subsequently walked several times up and down the hospital halls during the first three post operative days. Although I had pain with movement I had no pain at rest.

On the day after surgery my CRP (C reactive protein) was 0.2 mg/dl. CRP is a measure of inflammation in the body. Normal range is zero to 0.5. I was elated. One day after a major traumatic event which typically initiates an inflammatory cascade, I did not have excess inflammation throughout my body as measured by CRP. My WBC (white blood cell count) was also normal.

A paleo lifestyle will not prevent pain after surgery but being in a low inflammatory state before surgery certainly helped with recovery.

My walking ability immediately after surgery and during the next three days astounded the physical therapists and nurses. They all stated I had set records.

My colleagues in the Anesthesia Department could not believe that I received no opiate or NSAID pain medications during my recovery. It is now five days since surgery. I have taken no opiate pain killers or NSAIDs except for low dose aspirin (starting yesterday) to help prevent blood clots

I avoided NSAIDs because NSAIDs increase intestinal permeability (which leads to an inflammatory response) and also because NSAIDs increase risk of cardiovascular events (heart attack, stroke, blood clots in the legs which can travel to the lungs and cause death in severe cases)

I can attribute my success to many factors including an excellent anesthetic, a great surgeon, an optimal pre-operative medication protocol, the superb nursing and therapy staffs and the Paleo lifestyle. In preparing for surgery I was able to make an effective come back from a stressful travel week, two successive nights of sleep deprivation and an upper respiratory infection only because of the Paleo approach.

As I walked my laps around the orthopedic unit I noticed that most patients spent the entire day in bed except for a few laps each day with PT. Many factors contribute to that problem. Our PT department is very aggressive but post operative pain, obesity, inflammatory diets and sedentary lifestyles all contribute to slow recovery. The hospital menu is highly inflammatory thick with processed-carbohydrates, pro-inflammatory grains, legumes, and refined vegetable oils, and yes,  even some trans fats. A strictly Paleo menu would be very helpful. But most of those patients have been living the Standard American Lifestyle (inflammatory diet, chronic sleep deprivation, inadequate exercise, poor stress management, etc.)  for a lifetime prior to surgery and it can take months to years of a Paleo lifestyle to mitigate a lifetime of self abuse. Even then some damage is permanent (like my hip).

I ate the hospital’s fresh fruit, vegetables and wild seafood, the rest was delivered from home by my loving spouse. Kathie is my anchor in the storm and my guiding light when I become lost. The importance of love and human physical contact is well recognized by the Paleo community so it is appropriate that I end with an expression of gratitude to Kathie and the host of friends who visited me during recovery. Hugs and kisses are as important as an anti-inflammatory diet.

Live clean and prosper.

Bob Hansen MD

Paleolithic Diet Reversed Osteoporosis and Fatty Liver in an 82 year old man

Joe (not his real name) is an 82 year old man who presented to me in 2009 with severe degenerative arthritis of the spine, debilitating chronic pain,  osteoporosis, coronary artery disease, congestive heart failure and fatty liver. When I first met him in 2009 he weighed 265 pounds (6 foot), had just undergone multi-vessel coronary artery bypass surgery. He could not walk more than 30 feet without feeling short of breath and severe low back pain. He was referred to me for interventional pain management. At that time the only way he could sleep was in a hospital bed with his head elevated to a 90 degree angle. Otherwise he experienced “orthopnea” (shortness of breath lying flat caused by congestive heart failure). His osteoporosis (demineralization of bone) was so bad it was difficult to do pain blocks using X-RAY because the bone did not show up well on X-Ray due to the osteoporosis. He had also suffered compression fractures in the lumbar spine. Compression fractures are caused by weak bones where just the weight of the body can cause one or more vertebrae to partially collapse.

I recommended a paleolithic-carbohydrate restricted diet. He lost 90 pounds and on the paleo diet was able to get off some of his medication for congestive heart failure.

I saw Joe yesterday for an interventional pain management procedure (radio-frequency ablation of nerves to his painful arthritic lower lumbar facet joints). He gets these about every 6 months to treat chronic pain.

I recalled the first time I did this procedure. It was a struggle because his bones were so demineralized. But yesterday it was a breeze, his bones looked 30 years younger and had enough calcium and other minerals to provide beautiful fluoroscopic (live X-ray) images.

Joe is now sleeping with just 10 degrees elevation at the head of his bed (previously 90 degrees). His fatty liver disease is gone.

The Paleo diet allowed this elderly gentleman to lose 90 pounds, improve his exercise tolerance dramatically (he just won a metal detecting contest competing against young adults) and significantly improve his bone strength. It also cured his fatty liver disease.

Not bad for just limiting food to fresh vegetables, fresh fruits, meat, seafood, nuts and eggs.

Joe’s improvement is not a surprise. A study done at UCSF on the metabolic ward demonstrated improved calcium metabolism (reduced urinary excretion of calcium)  within 2 weeks of placing young “couch potato” adults on a paleolithic diet. It also demonstrated improvements in blood pressure, glucose tolerance, decreased insulin secretion, increased insulin sensitivity and improved lipid profiles in just a few weeks. This occurred without an exercise program (exercise will enhance bone strength, reduce blood pressure, improve insulin sensitivity and improve lipid profiles) and without weight loss. The subjects were “force fed” to avoid weight loss so the beneficial effects of the dietary change alone could be analyzed without the con-founder of weight loss. You can read the abstract of this study here.

The improvements in calcium metabolism are not mentioned in the abstract but appear in the full article in Table 1.

Joe is very grateful for the tremendous improvement in his quality of life, primarily achieved by adopting a Paleo-diet.

Until next time.

BOB Hansen MD

Low Carb Beats Low Fat Again, Annals of Internal Medicine article

Once again, a randomized trial demonstrates that a carbohydrate restricted approach is superior to a low fat diet with regards to weight loss, inflammation, body composition and cardiovascular risk factors. This study was recently published in the Annals of Internal Medicine, the official journal for the American College of Physicians.

Men and women aged 22 to 75 years with a body mass index of 30 to 45 kg/m2 (obesity defined as BMI > 30, morbid obesity defined as BMI >35) were recruited from the general public by using mailing lists, fliers, work site and community screenings, and television advertisements.

Neither diet included a specific calorie or energy goal. Participants in each group were asked to refrain from changing their physical activity levels during the intervention

Here is the summary cut and pasted from the abstract.

Objective: To examine the effects of a low-carbohydrate diet compared with a low-fat diet on body weight and cardiovascular risk factors.

Design: A randomized, parallel-group trial. (ClinicalTrials.gov: NCT00609271)

Setting: A large academic medical center.

Participants: 148 men and women without clinical cardiovascular disease and diabetes.

Intervention: A low-carbohydrate (<40 g/d) or low-fat (<30% of daily energy intake from total fat [<7% saturated fat]) diet. Both groups received dietary counseling at regular intervals throughout the trial.

Measurements: Data on weight, cardiovascular risk factors, and dietary composition were collected at 0, 3, 6, and 12 months.

Results: Sixty participants (82%) in the low-fat group and 59 (79%) in the low-carbohydrate group completed the intervention. At 12 months, participants on the low-carbohydrate diet had greater decreases in weight (mean difference in change, −3.5 kg [95% CI, −5.6 to −1.4 kg]; P = 0.002), fat mass (mean difference in change, −1.5% [CI, −2.6% to −0.4%]; P = 0.011), ratio of total–high-density lipoprotein (HDL) cholesterol (mean difference in change, −0.44 [CI, −0.71 to −0.16]; P = 0.002), and triglyceride level (mean difference in change, −0.16 mmol/L [−14.1 mg/dL] [CI, −0.31 to −0.01 mmol/L {−27.4 to −0.8 mg/dL}]; P = 0.038) and greater increases in HDL cholesterol level (mean difference in change, 0.18 mmol/L [7.0 mg/dL] [CI, 0.08 to 0.28 mmol/L {3.0 to 11.0 mg/dL}]; P < 0.001) than those on the low-fat diet.

Limitation: Lack of clinical cardiovascular disease end points.

Conclusion: The low-carbohydrate diet was more effective for weight loss and cardiovascular risk factor reduction than the low-fat diet.

Primary Funding Source: National Institutes of Health.

Let’s go through those results again: At 12 months, participants on the low-carbohydrate diet had

  1.  greater decreases in weight. This has been demonstrated in multiple previously published studies.
  2.  greater decreases in  fat mass. This is an important distinction, the low carb group lost more fat, not muscle.
  3.  greater decreases in the ratio of total to high-density lipoprotein (HDL) cholesterol. This ratio is a measure of cardiovascular risk (risk for heart attack and stroke). It improved more on low carb than on low fat diets.
  4.  greater decreases in triglyceride level. Triglyceride level is also an important cardiovascular risk factor. It went down significantly more as compared to the low fat diet.
  5.  greater increases in HDL cholesterol level. This result is considered to be protective against heart attack and stroke.
  6. greater decreases in CRP level than those in the low-fat group. CRP (C-reactive protein) is a blood test for inflammation and is also a cardiovascular risk factor.
  7. significant decreases in estimated 10-year risk for coronary heart disease as measured by the Framingham risk analysis at 6 and 12 months, whereas those in the low-fat group did not. Say again, the low fat group did not decrease their Framingham risk analysis but the low carb group did.

All of these differences were “statistically significant”, meaning they were unlikely caused by accident.
And what about side-effects?

The number of participants who had symptoms, including constipation, fatigue, thirst, polyuria, diarrhea, heartburn, gas, nausea, vomiting, appetite changes, or headache, did not differ significantly between the low-carbohydrate and low-fat groups, except significantly more participants on the low-fat diet reported headaches at 3 months

The authors concluded:

Our study found that a low-carbohydrate diet induced greater weight loss and reductions in cardiovascular risk factors at 12 months than a low-fat diet among black and white obese adults who did not have diabetes, CVD, or kidney disease at baseline. Compared with a low-fat diet, a low-carbohydrate diet resulted in greater improvements in body composition, HDL cholesterol level, ratio of total–HDL cholesterol, triglyceride level, CRP level, and estimated 10-year CHD risk. Because CVD is the most common cause of death in the United States and obesity is a particularly prevalent risk factor, our study has important clinical and public health implications

Effects of Low-Carbohydrate and Low-Fat Diets: A Randomized Trial, A. Bazzano, MD, PhD, MPH et. al., Ann Intern Med. 2014;161(5):309-318. doi:10.7326/M14-0180

Get rid of the sugar-added foods, processed and refined flour foods and vegetable oils. Send a message to corporate America that crap-in-a bag and crap-in-a-box is no longer in demand. Eat only grass-fed meat, wild seafood, fresh vegetables, fresh fruit and tree nuts. Enjoy better health and better food.


Bob Hansen MD.